
Corneal Pigment Tattooing Versus Biological Stromal Depigmentation: A Structured Comparative Review of Keratopigmentation and Lumineyes™ Laser Iris Depigmentation
Anatomical target, pigment biology, optical consequences, corneal integrity, intraocular-pressure considerations, diagnostic accessibility, evidence quality, and long-term research priorities.

Quick Answer
Keratopigmentation (KTP) and Lumineyes™ do not change eye color in the same way. KTP places exogenous pigment within the corneal stroma, creating an artificial visible color layer anterior to the native iris. Lumineyes™ instead targets endogenous visible pigmentation within the anterior iris and is structured around selective stromal melanin modulation , controlled treatment-related pigment response, and response-guided staged treatment.
Contemporary KTP has a larger published evidence base and has demonstrated generally favorable visual-acuity outcomes in selected patients, although changes in contrast sensitivity, endothelial measurements, retreatment requirements, and rare corneal biomechanical complications have been reported. Published laser iris depigmentation evidence is smaller and heterogeneous, with both favorable series and serious pigment-related complications reported after particular protocols. Therefore, comparisons must remain procedure-specific, evidence-specific, and anatomically precise.
Abstract
Background: Elective alteration of apparent eye color includes procedures that may produce a superficially similar cosmetic endpoint while interacting with entirely different ocular tissues. Modern corneal keratopigmentation introduces exogenous pigment into the corneal stroma. Laser iris depigmentation acts instead on endogenous iris pigmentation. Treating these interventions as interchangeable obscures clinically important differences in tissue modification, optical architecture, pigment biology, monitoring requirements, and future diagnostic access.
Objective: To compare contemporary cosmetic keratopigmentation with the Lumineyes™ clinical framework for selective laser iris depigmentation, focusing on anatomical target, optical pathway preservation, corneal structure, endothelial considerations, pigment-associated biological response, intraocular-pressure dynamics, diagnostic accessibility, durability, and the relative maturity of the available evidence.
Evidence synthesis: Modern femtosecond-assisted KTP has published prospective and longitudinal data demonstrating high cosmetic satisfaction and generally preserved conventional visual outcomes in selected patients. However, retreatment, photic symptoms, pigment fading or color change, modest endothelial-cell-count changes, contrast sensitivity changes, and postoperative ectatic progression have also been reported. Laser iris depigmentation has a smaller and more heterogeneous evidence base. A prospective 1,176-eye series reported favorable outcomes with one defined 532-nm protocol, whereas severe pigmentary glaucoma has been reported after other cosmetic iris laser treatments. Such findings demonstrate the importance of procedural characterization rather than universal attribution across all laser protocols.
Conclusion: The principal distinction between KTP and Lumineyes™ is not simply surgical versus laser treatment. KTP changes the observer's view of the iris through corneal optical masking, while Lumineyes™ seeks biological modification of native iris pigmentation. The theoretical tissue-preservation advantages of avoiding corneal pigment implantation require continued prospective validation and should not be substituted for head-to-head clinical outcome evidence.
1. Introduction
Elective eye-color modification occupies an unusual position within ophthalmology: the desired endpoint is aesthetic, while the anatomical structures involved are essential to visual function. For this reason, conventional cosmetic endpoints alone are insufficient. Tissue preservation, optical quality, pressure response, long-term surveillance, and the ability to diagnose unrelated future ocular disease remain central clinical considerations.
Contemporary discussions generally include three broad strategies: cosmetic iris implants, corneal keratopigmentation, and laser eye color change through iris depigmentation. The present review deliberately focuses on the two non-implant approaches: corneal keratopigmentation and the Lumineyes™ iris-based approach.
Their visible objective may appear similar, but their anatomical logic is opposite. Keratopigmentation changes what the observer sees by placing a colored material anterior to the iris. Iris depigmentation attempts to change the visible pigmentation of the native iris itself.
2. Anatomical Target and Mechanism of Visible Color Change
Keratopigmentation (KTP)
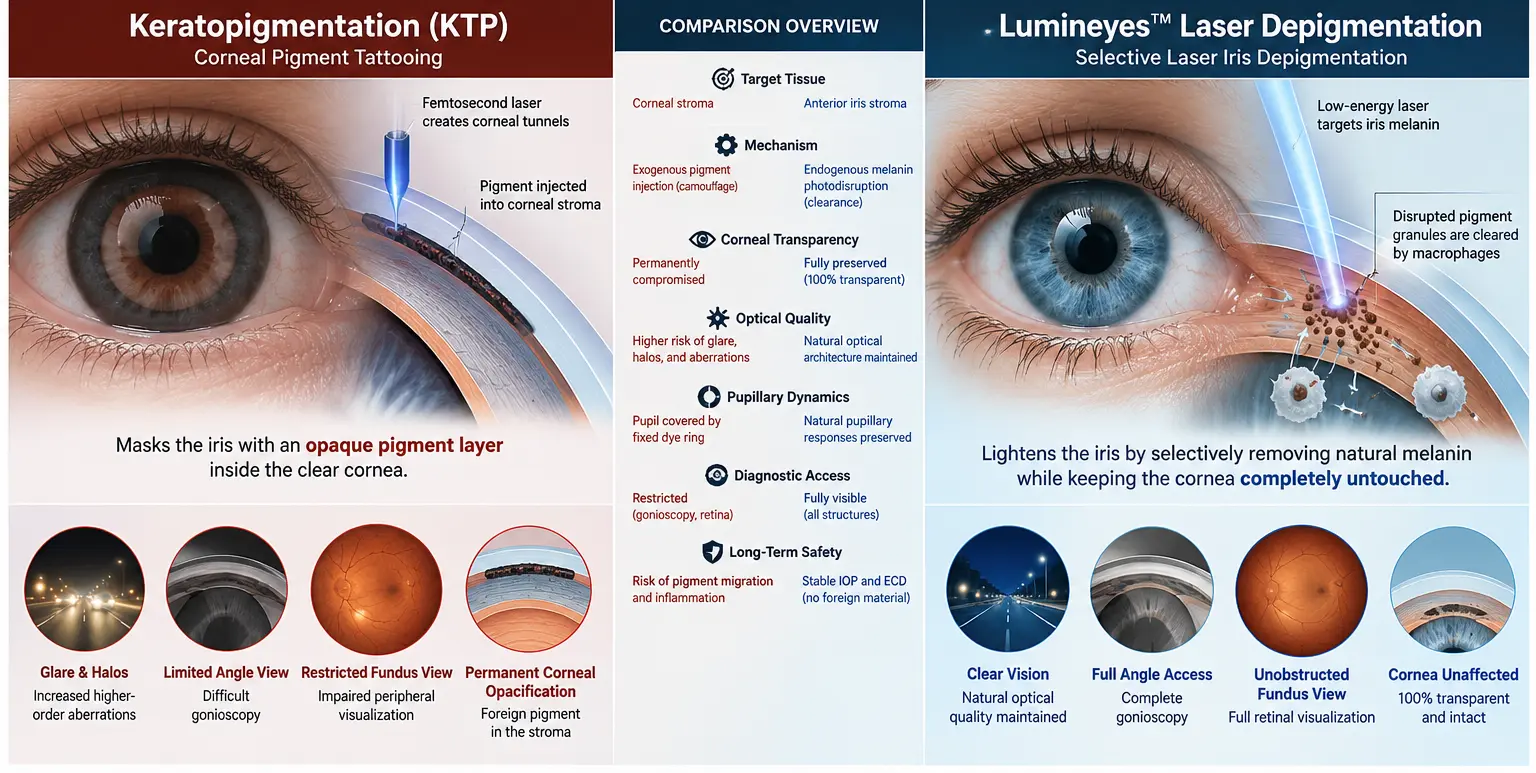
Modern cosmetic KTP typically creates an intrastromal corneal plane or tunnel, frequently with a femtosecond laser, into which micronized pigment is introduced. The resulting pigmented corneal annulus lies anterior to the native iris and alters its visible appearance.
Lumineyes™
Lumineyes™ is designed to act through the transparent cornea on pre-existing visible anterior iris pigmentation. No artificial color pigment is intentionally deposited within the corneal stroma; visible change instead depends on staged modification of endogenous iris melanin and subsequent biological response.
| Domain | Keratopigmentation | Lumineyes™ |
|---|---|---|
| Primary tissue | Corneal stroma | Visible anterior iris pigmentation |
| Pigment source | Exogenous pigment | Endogenous iris melanin |
| Visible strategy | Optical masking / camouflage | Biological pigment modulation |
| Corneal tunnel/pocket | Usually required for intrastromal KTP | Not required |
| Artificial corneal color layer | Created intentionally | Not created |
| Native iris pigment | Not the treatment target | Primary visible biological target |
| Main safety domain | Corneal structure, pigment behavior, optics and biomechanics | Pigment response, inflammation, aqueous outflow and IOP monitoring |
A related biological analysis is available in the Research Archive: Biological Fate of Pigment in Cosmetic Iris Color Modification . That analysis focuses specifically on endogenous melanin modulation versus exogenous pigment deposition and provides the biological context for the present anatomical comparison.
3. The Evidence Landscape Is Unequal
The published evidence base is not equally mature for the two approaches. Keratopigmentation has a longer history and includes experimental work, reviews, prospective cohorts, medium- and long-term cosmetic series, and contemporary optical-outcome studies.
Laser iris depigmentation has substantially fewer independent clinical publications. Importantly, the available studies do not describe one standardized intervention. Different laser platforms, wavelengths, pulse characteristics, treatment densities, inter-session intervals, patient-selection strategies, medications, and monitoring protocols may all be grouped under the broad term laser iris depigmentation.
This heterogeneity is central to interpretation. The Research Archive therefore uses the principle described in How to Interpret Safety Claims in Laser Eye Color Change : a clinical event should first be attributed to the procedure in which it was actually observed, before being generalized to another technique.
| Evidence | Design / Population | Principal finding | Interpretation |
|---|---|---|---|
|
Peer reviewed D'Oria et al., 2021 | 79 eyes / 40 patients; cosmetic KTP; mean follow-up 29 months | High cosmetic satisfaction; retreatments common; photophobia, color change, fading and one visual-field limitation reported. | Supports effectiveness while demonstrating that durability and optical symptoms remain clinically relevant. |
|
Peer reviewed Alio et al., 2025 | Prospective consecutive series; 166 cosmetic KTP eyes | No significant group-level deterioration in VA, IOP, visual-field MD or measured HOAs at 12 months; modest ECD reduction and contrast-sensitivity changes reported. | Does not support simplistic claims that contemporary KTP inevitably produces major HOA deterioration. |
|
Peer reviewed Nouzovská et al. | Case series; 5 patients / 10 eyes after cosmetic KTP | Progressive ectatic corneal changes were documented after treatment. | Establishes corneal biomechanics as a relevant surveillance domain, but does not establish population incidence. |
|
Peer reviewed Grimaldos Ruiz, 2021 | Prospective PCI series; 1,176 eyes | Favorable efficacy and satisfaction; no significant long-term group-level change in corrected vision or IOP; transient delayed iritis reported. | Evidence pertains to the specific PCI protocol studied and should not be generalized automatically to every LID technique. |
|
Peer reviewed Liu et al., 2023 | Case report after four bilateral cosmetic iris laser sessions | Severe bilateral pigmentary glaucoma with very high presenting IOP was reported. | Demonstrates that uncontrolled or protocol-specific pigment response may produce serious complications; procedural equivalence with other methodologies cannot be assumed. |
|
First-party clinical record MyLumineyes longitudinal dataset | Retrospective real-world clinical observation | Longitudinal observations regarding treatment response, IOP and adverse events are documented within the Research Archive. | Useful procedure-specific evidence, but not randomized and not a substitute for independent prospective validation. |
The procedure-specific Lumineyes™ dataset and its methodological boundaries are discussed separately in MyLumineyes Clinical Data and Long-Term Observation . Keeping first-party clinical evidence separate from independent literature is essential to preserve evidentiary clarity.
4. Optical Quality: Artificial Corneal Aperture Versus Native Pupillary Optics
Because the cornea is a principal refractive interface, the optical consequences of modifying its transparency must be considered independently from standard high-contrast visual acuity.
Modern KTP data require a nuanced interpretation. The 2025 prospective series of 166 eyes did not demonstrate statistically significant deterioration in measured coma, trefoil, spherical aberration, or total higher-order aberrations at 12 months. However, mean endothelial-cell count decreased and contrast sensitivity decreased across mesopic spatial frequencies, with selected photopic changes reaching statistical significance.
Earlier longitudinal KTP data similarly demonstrated strong cosmetic satisfaction while documenting early light sensitivity, pigment fading or color change, frequent retreatment in some patients, and visual-field limitation in an individual with a relatively small artificial pupil.
The relevant scientific question is therefore not whether KTP universally causes optical deterioration—it does not appear to do so—but whether conventional acuity measurements capture all consequences of placing a fixed pigmented annulus within the corneal optical system.
Lumineyes™ does not intentionally create a second corneal aperture. The native pupil therefore remains the optical aperture. This provides a mechanistic rationale for preserving natural corneal transmission, but it should not be converted into an unsupported assertion that every component of optical quality has already been prospectively demonstrated to remain unchanged.
5. Corneal Integrity, Endothelium, and Biomechanics
5.1 Endothelial assessment
Any elective procedure performed in a healthy eye should be evaluated for potential effects on the corneal endothelium. In contemporary cosmetic KTP data, a modest decrease in mean endothelial-cell density has been reported. The clinical meaning of such a change depends on measurement reproducibility, baseline reserve, age, and longer-term follow-up.
Lumineyes™ does not intentionally introduce pigment into the corneal stroma. This removes one potential optical obstacle to corneal imaging, but absence of implanted corneal pigment should not be treated as a substitute for objective endothelial safety measurement. Serial specular microscopy remains an appropriate outcome for prospective study.
5.2 Corneal biomechanics
Intrastromal KTP requires lamellar manipulation of the cornea. A published case series has documented progressive corneal ectatic changes after purely cosmetic femtosecond-assisted KTP. These reports establish biological plausibility and clinical relevance, although they do not determine the incidence of ectasia among all treated patients and may include additional modifying factors.
Lumineyes™ does not require creation of a corneal flap, stromal pocket, or tunnel, and therefore does not share this specific biomechanical intervention.
6. Pigment Biology, Inflammation, and Intraocular Pressure
The principal biological safety domain of iris depigmentation is fundamentally different from that of KTP. Laser treatment of visible iris pigmentation can release endogenous pigment into the anterior segment. The clinical significance of that response depends not only on whether pigment is released, but on its quantity, timing, distribution, inflammatory response, aqueous-humor dynamics, and the individual eye's outflow capacity.
Experimental 532-nm work in pigmented rabbit eyes demonstrated reduction of iris pigment with transient low-grade anterior-chamber inflammation and no significant IOP elevation under the studied conditions. In humans, the 1,176-eye PCI series reported no significant long-term group-level IOP difference, while delayed transient iritis was described.
Conversely, severe pigmentary glaucoma following cosmetic iris laser treatment has also been reported. These findings should neither be ignored nor indiscriminately applied to every iris-depigmentation protocol.
This is the rationale behind the Lumineyes™ concepts of controlled treatment-related pigment response and response-guided staged treatment. A more detailed procedural discussion is available in Laser Iris Depigmentation — Clinical Perspective .
7. Diagnostic Accessibility and Future Ophthalmic Care
Diagnostic access is particularly important in elective procedures performed on healthy eyes because recipients may later develop glaucoma, cataract, retinal disease, corneal disease, or other unrelated age-associated pathology.
A corneal pigment layer can alter the line of sight through the treated region. The magnitude of this effect depends on pigment density, tunnel geometry, aperture diameter, pupillary dilation, examination technique, and the structure being visualized. It is therefore inappropriate to state that gonioscopy or fundus examination becomes universally impossible after KTP.
The more defensible anatomical statement is that a permanently pigmented corneal region has the potential to alter visualization through that region and may complicate selected diagnostic or surgical views.
Lumineyes™ does not intentionally establish a persistent pigmented barrier within the corneal optical pathway. Gonioscopy, anterior-segment imaging, specular microscopy, slit-lamp examination, and posterior-segment visualization therefore retain the native transparent corneal route, assuming no unrelated pathology or transient postoperative condition limits visualization.
8. Durability, Retreatment, and the Meaning of “Permanent”
Permanence should be defined carefully for both techniques.
In KTP, implanted pigment may remain within the cornea for prolonged periods, but published studies show that persistent pigment does not eliminate the need for retreatment. In the 2021 longitudinal cosmetic KTP series, 35.4% of eyes underwent reoperation, largely for additional cosmetic refinement. Color fading and color change were also reported in a minority of cases.
Removal or modification of implanted pigment may be possible, but it should not be described as trivial reversal because additional corneal intervention may be required.
Lumineyes™ presents a different question. No artificial pigment requires later removal; however, long-term phenotype stability depends on the biology of residual iris pigmentation, stromal architecture, ageing, individual response, and other factors. Exact future color therefore should not be guaranteed.
The appropriate scientific endpoint is objective long-term stability measured through standardized photography, colorimetry, iris mapping, and longitudinal structural assessment—not the use of the word “permanent” as a substitute for measurement.
9. Comparative Clinical Matrix
| Parameter | Keratopigmentation | Lumineyes™ |
|---|---|---|
| Primary target | Corneal stroma | Visible anterior iris pigmentation |
| Method of color change | Exogenous pigment creates an artificial visible color layer | Native visible iris pigment is selectively modulated |
| Foreign pigment | Intentionally implanted | Not intentionally implanted |
| Corneal stromal dissection | Yes, in femtosecond/intrastromal techniques | No stromal tunnel or pocket |
| Native iris pigmentation | Preserved behind the corneal pigment layer | Direct treatment target |
| Artificial visible aperture | Generally present as central clear corneal zone | No artificial corneal aperture |
| Pupillary physiology | Native pupil remains mobile behind fixed corneal geometry | Native pupil remains the primary optical aperture |
| Visual acuity evidence | Generally stable in contemporary published cohorts | Published LID evidence limited and protocol-dependent |
| Higher-order aberrations | No significant group-level deterioration in recent 12-month study | Insufficient Lumineyes-specific prospective wavefront data |
| Contrast sensitivity | Reductions reported in recent prospective study | Prospective protocol-specific data required |
| Endothelium | Small mean ECD reduction reported in contemporary prospective cohort | No corneal pigment implantation; objective serial ECD validation still required |
| Corneal biomechanics | Stromal intervention; postoperative ectasia cases reported | No corneal tunnel/flap created |
| Primary biological concern | Corneal wound response, pigment behavior, optics and biomechanics | Pigment release, inflammation, IOP and aqueous-outflow response |
| IOP | Sustained pressure elevation not a dominant signal in published cosmetic KTP cohorts | Requires active monitoring because severe pigment-related IOP elevation has been reported after some LID protocols |
| Diagnostic optical barrier | Possible through pigmented corneal regions | No intentionally implanted corneal pigment barrier |
| Color predictability | Relatively high because color is externally introduced | Biologically constrained by native iris phenotype and individual response |
| Retreatment | Touch-up procedures reported | Further exposure is intended to be response-guided rather than cosmetically predetermined |
| Evidence maturity | Greater published clinical evidence | Smaller and heterogeneous published evidence base; Lumineyes-specific validation ongoing |
10. Camouflage Versus Biological Modification
The most useful distinction between the procedures is not “surgery versus laser.” It is camouflage versus biological modification.
KTP changes the visible phenotype by placing a selected artificial color anterior to the iris. This provides substantial control over the intended cosmetic appearance, but requires deliberate modification of the transparent corneal stroma.
Lumineyes™ accepts greater biological variability because the final phenotype depends on the patient's native iris architecture. Rather than selecting and implanting a color, treatment seeks to reduce visible pigment sufficiently for underlying structural and optical characteristics to become more apparent.
This explains why an exact final color should not be guaranteed within a biological depigmentation model.
11. Why Lumineyes™ Should Not Be Treated as Synonymous With Generic LID
“Laser iris depigmentation” is a category, not a single standardized intervention. Two treatments may both involve laser exposure of iris pigment while differing in platform, wavelength, pulse duration, spot diameter, energy, exposure density, treatment geometry, session interval, cumulative burden, medication, patient selection, and clinical criteria for subsequent treatment.
The Lumineyes™ framework is defined in this Research Archive by three related concepts:
- Selective stromal melanin modulation — preferential interaction with visible pre-existing stromal pigmentation while minimizing unnecessary interaction with surrounding structures.
- Controlled treatment-related pigment response — recognition that released pigment and the subsequent anterior-segment response are clinically relevant treatment variables.
- Response-guided staged treatment — subsequent exposure is determined by clinical response rather than an obligation to complete a predetermined fixed number of laser sessions.
These concepts are described in greater detail in Selective Stromal Melanin Modulation and should be considered proposed clinical and procedural terminology rather than independently validated histopathological classifications.
| Domain | Variables that should be reported |
|---|---|
| Laser system | Platform, wavelength, pulse characteristics and spot geometry |
| Exposure | Energy range, density, treated area and cumulative exposure |
| Staging | Number of sessions, interval between sessions and criteria for re-exposure |
| Baseline ocular status | IOP, gonioscopy, anterior segment, endothelium, iris phenotype and relevant risk factors |
| Biological response | Anterior-chamber pigment/cells, inflammation, corneal response and IOP kinetics |
| Medication | Pre-treatment, immediate post-treatment and follow-up regimen |
| Follow-up | Timing, completeness, duration, loss to follow-up and predefined adverse-event definitions |
| Outcomes | VA, contrast sensitivity, wavefront data, ECD, IOP, gonioscopy, AS-OCT and standardized iris imaging |
12. Research Priorities
Direct comparison between KTP and Lumineyes™ should move beyond cosmetic photographs and standard visual acuity. A meaningful comparative protocol should include objective measurements across multiple ophthalmic domains.
- Uncorrected and corrected visual acuity
- Manifest refraction
- Photopic and mesopic contrast sensitivity
- Glare disability testing
- Wavefront aberrometry and higher-order aberrations
- Photopic and mesopic pupillometry
- Corneal tomography and pachymetry
- Serial central and peripheral endothelial-cell assessment
- Gonioscopy and anterior-segment OCT
- Time-resolved intraocular-pressure measurements
- Standardized iris photography and colorimetry
- Objective documentation of diagnostic visibility
- Patient-reported optical-quality outcomes
- Long-term retreatment burden
- Longitudinal follow-up extending beyond five years
Prospective Lumineyes™ research should particularly focus on validating the relationship between treatment-related pigment response, early anterior-segment findings, intraocular-pressure kinetics, endothelial safety, and objective readiness for subsequent exposure.
13. Limitations of the Current Comparison
Several limitations prevent categorical claims of comparative superiority.
- No randomized or matched prospective head-to-head study comparing contemporary cosmetic KTP with Lumineyes™ has been published.
- The KTP literature is larger and more mature than the protocol-specific Lumineyes™ literature.
- Anatomical preservation arguments are not equivalent to demonstrated long-term comparative clinical outcomes.
- Laser iris depigmentation studies are procedurally heterogeneous.
- Serious complications reported after one LID procedure cannot automatically establish the incidence of that complication after a materially different laser protocol.
- Conversely, favorable results obtained with one laser methodology cannot establish universal safety for all iris-depigmentation techniques.
- Operator experience, patient selection, monitoring and postoperative management may materially influence outcomes in both procedural categories.
- First-party Lumineyes™ longitudinal observations require prospective and independent validation.
14. Conclusions
Cosmetic keratopigmentation and Lumineyes™ selective iris depigmentation should not be described as interchangeable methods of accomplishing the same procedure. They achieve visible color change through fundamentally different anatomical strategies.
Contemporary KTP has a meaningful published evidence base and generally favorable conventional visual outcomes in selected patients. Its mechanism nevertheless requires intentional modification of the corneal stroma with exogenous pigment, and the literature documents clinically relevant issues including retreatment, photic symptoms, contrast-sensitivity changes, endothelial-cell-count changes, pigment-related cosmetic evolution, and rare postoperative ectatic progression.
Lumineyes™ instead seeks controlled modification of native anterior iris pigmentation without intentionally establishing an artificial pigment layer within the cornea. Its central safety problem is consequently different: the controlled management of treatment-related pigment response, inflammation, aqueous-outflow behavior, and intraocular pressure.
The present evidence supports a clear anatomical and mechanistic distinction. It does not yet justify a universal claim that one intervention is clinically superior to the other in every patient or across every outcome.
The next scientific step is therefore not stronger promotional language, but stronger measurement: standardized optical testing, objective corneal and iris imaging, endothelial surveillance, time-resolved IOP monitoring, transparent adverse-event reporting, and sufficiently long prospective follow-up.
Lumineyes™ seeks to modify the native pigment visible through that window. Their risks, monitoring requirements and evidence should therefore be evaluated according to the tissue each procedure actually changes.
References
- D'Oria F, Abu-Mustafa SK, Alio JL. Cosmetic Change of the Apparent Color of the Eye: A Review on Surgical Alternatives, Outcomes and Complications. Ophthalmology and Therapy. 2022;11:465–477. DOI: 10.1007/s40123-022-00458-2. PubMed
- Hasani H, Es'haghi A, Rafatnia S, Alilou S, Abolmaali M. Keratopigmentation: a comprehensive review. Eye. 2020;34:1039–1046. DOI: 10.1038/s41433-019-0750-2. PubMed
- D'Oria F, Alio JL, Rodriguez AE, Amesty MA, Abu-Mustafa SK. Cosmetic Keratopigmentation in Sighted Eyes: Medium- and Long-term Clinical Evaluation. Cornea. 2021;40:327–333. DOI: 10.1097/ICO.0000000000002417. PubMed
- Alio J, Sanginabadi A, Hojabr AT, Jafari B. Femtosecond laser-assisted keratopigmentation outcomes for pure cosmetic purposes. American Journal of Ophthalmology Case Reports. 2025;38:102297. DOI: 10.1016/j.ajoc.2025.102297. PubMed
- Nouzovská K, Barazandeh Noveyri B, Abu-Mustafa SK, Alió JL. Corneal Ectasia Following Cosmetic Keratopigmentation. Cornea. 2025;44(6):779–787. DOI: 10.1097/ICO.0000000000003754. PubMed
- Grimaldos Ruiz P. Photoablative cosmetic iridoplasty: effective, safe, and predictable—eye color change in 1176 eyes. International Ophthalmology. 2021;41:1381–1393. DOI: 10.1007/s10792-021-01693-5. PubMed
- Yildirim Y, Duzgun E, Kar T, et al. Evaluation of Color-Changing Effect and Complications After Nd:YAG Laser Application on Iris Surface. Medical Science Monitor. 2016;22:107–114. PubMed
- Liu J, Korban S, Moster MR, Rhéaume MA, Wang Q. Bilateral severe iatrogenic pigmentary glaucoma following laser treatment for cosmetic iris color change. American Journal of Ophthalmology Case Reports. 2023;32:101927. DOI: 10.1016/j.ajoc.2023.101927. PubMed
- D'Oria F, Alio JL. Surgical Techniques for Cosmetic Eye Color Change: A Narrative Review. Ophthalmology and Therapy. 2025;14:1685–1694. DOI: 10.1007/s40123-025-01177-0. PubMed
